A patient in a metro area with six oncologists can get a second opinion by making a phone call. A patient in a rural county served by one might have to drive three hours, wait weeks, and pay out of pocket to hear from anyone else at all.
Second opinions are harder to get in areas with fewer specialist options because the same small pool of clinicians shares referral patterns, records systems, and often training backgrounds, which narrows the range of independent judgment available and adds travel, wait-time, and cost barriers that denser markets don’t face.
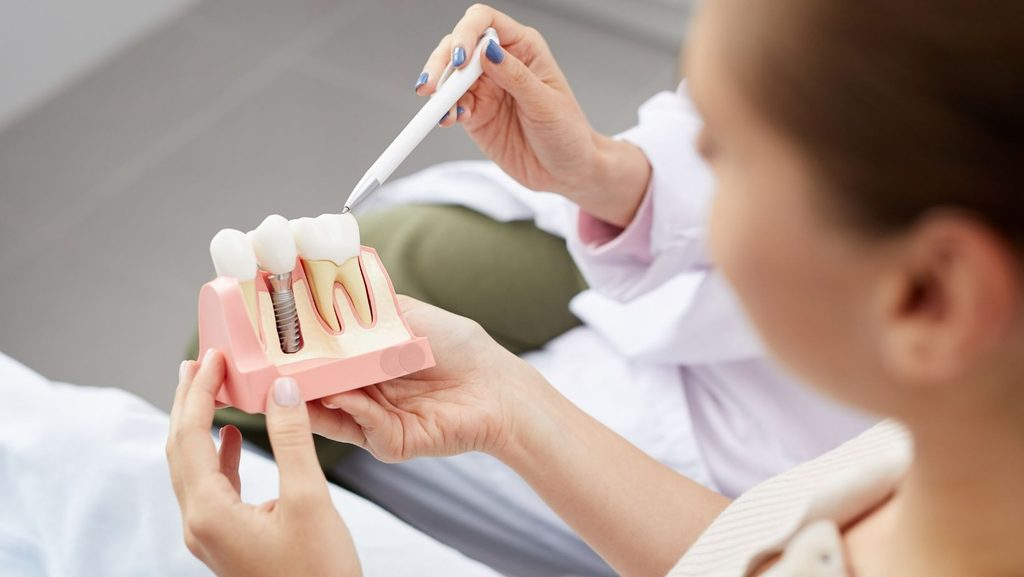
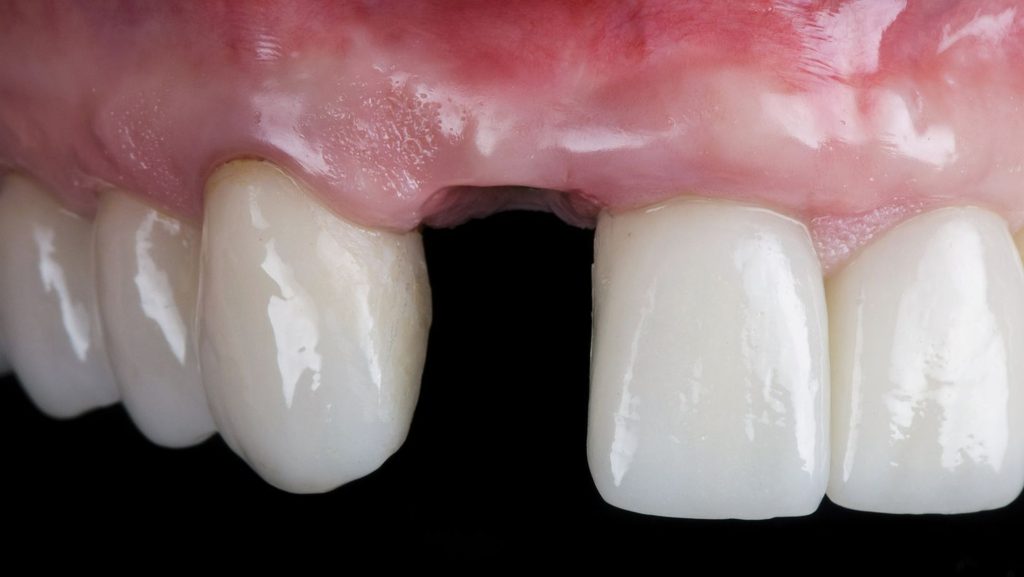
Specialist density runs as high as 263 per 100,000 residents in urban areas and as low as 30 per 100,000 in rural ones. That gap changes not just how far someone drives, but whether a genuinely independent second view exists nearby. In a dense market, someone weighing dental implant surgery in Inglewood, CA can compare several surgeons within a short drive; in a thinly served rural county, that choice may not exist at all.
Studies on patient-initiated second opinions show they change diagnosis, treatment, or prognosis in a substantial share of cases, sometimes reported as high as two-thirds. When the local specialist bench is thin, fewer patients get the chance to find out if their case is one of them.
How Specialist Shortages Limit Access to Another Medical View
Fewer specialists in a region mean fewer truly independent opinions, because the clinicians available often trained together, refer to one another routinely, or work for the same health system. Geography, referral habits, and urgency all compound the problem for patients trying to get an outside look at a diagnosis.
Why a Small Referral Network Can Reinforce the First Diagnosis
A tight referral network tends to echo the first opinion instead of challenging it. When a primary care doctor in a small market has one cardiologist or one oncologist to send patients to, that specialist’s judgment effectively becomes the only judgment in circulation.
Referrals within the same hospital system or physician group often share diagnostic protocols, case conferences, and even the same read of imaging or pathology. A second consultation in that setting can amount to a friendly confirmation rather than an independent review. Patients rarely realize how connected their “second” doctor is to their first until they ask directly about training background or institutional affiliation.
Which Patients Face the Greatest Geographic Barriers
Rural patients, older adults, and people with rare or complex conditions face the steepest climb to a genuine second opinion. Rural counties frequently have no subspecialist at all for conditions like pediatric cardiology, neuro-oncology, or maternal-fetal medicine, forcing a trip to the nearest metro area.
Patients without reliable transportation or paid time off feel this most acutely. A single specialist visit already means missed work; a second one, possibly hours away, can mean missing two or three days of income to get a second reading on a diagnosis.
Why Rural Travel, Wait Times, and Urgent Care Decisions Collide
Long travel distances and long wait times often force patients to decide between waiting for another opinion and starting treatment on the timeline offered. National specialist wait times have climbed toward the 26- to 31-day range on average, and rural referrals frequently stretch longer once travel and limited clinic days are factored in.
For a slow-growing condition, a delay of a few weeks to get another opinion carries little risk. For a fast-moving diagnosis, that same delay can force a patient to choose between proceeding with the only plan on the table or risking a treatment gap while pursuing outside review.
What Makes a Second Opinion Difficult to Arrange
A second opinion becomes hard to arrange when finding an unaffiliated expert, transferring records, and paying for the extra visit all present separate obstacles at once. Each piece, from locating the right specialist to convincing an insurer to cover the consult, adds friction that compounds in a limited-specialist market.
Finding an Independent Specialist With Relevant Expertise
Locating a specialist with no ties to the original treating physician is the first hurdle, and it gets harder as the regional pool of experts shrinks. In many small and mid-sized markets, most specialists in a given field trained at the same regional program or belong to the same hospital network, which limits how “independent” a local second opinion really is.
Patients often need to look outside their home region entirely, toward a state university medical center or a specialty-specific center of excellence, to find someone with no professional connection to the first doctor.
Obtaining Records, Imaging, and Pathology for Review
A useful second opinion depends on complete records, and gathering imaging, pathology slides, and lab results from a small local system can take weeks. Independent medical review, whether for a cancer diagnosis or a proposed surgery, hinges on the reviewing specialist being able to re-examine the same scans and tissue samples rather than relying on a written summary.
Small hospitals and clinics sometimes lack digital systems that make transferring files simple, so patients end up requesting physical copies of scans or paying courier fees to move pathology slides between facilities.
How Insurance Rules and Out-of-Pocket Costs Add Friction
Insurance plans vary widely on whether a second opinion requires a referral, prior authorization, or falls outside network coverage entirely. Whether a referral is necessary at all depends on the specific plan, and in areas with few in-network specialists, the only qualified reviewer available may be out of network by default.
That combination pushes many patients toward paying out of pocket. A limited number of free or low-cost second-opinion services exist for specific conditions like cancer, but coverage is inconsistent and application processes take time.
When Telehealth Can Expand Options and When It Cannot
Telehealth widens access to specialists outside the local area for consultations, chart reviews, and imaging-based second opinions, but it cannot replace an in-person exam, biopsy, or procedure that requires the specialist’s hands-on involvement. Virtual second-opinion programs run by academic medical centers now connect patients with subspecialists for conditions ranging from rare cancers to complex orthopedic injuries, often without requiring travel.
A remote specialist can review pathology, imaging, and records and issue a written opinion. Conditions requiring a physical exam, a new biopsy, or an in-person procedure still require local follow-up, which can be its own challenge in a low-specialist-density area.
Practical Ways to Pursue an Independent Review From a Limited-Market Area
Getting an independent review from a limited-specialist market starts with asking the current clinician for an out-of-network referral, then widening the search to academic centers and virtual second-opinion programs if local options run out. Knowing what to ask before committing to a remote specialist, and recognizing when a symptom needs immediate care instead of a delayed second opinion, rounds out a workable plan.
How to Ask Your Current Clinician for a Referral
Most physicians support patients seeking a second opinion and will provide a referral without hesitation. Framing the request plainly, such as “I’d like another specialist to review this before we move forward,” works better than avoiding the topic out of concern about offending the doctor.
Ask directly for a referral to someone outside the current practice or hospital system. A clinician who supports the request will often know of an academic center or an out-of-network expert suited to the specific diagnosis.
Using Academic Medical Centers and Virtual Second-Opinion Programs
Academic medical centers and dedicated virtual second-opinion programs give patients in low-specialist regions access to subspecialists who would otherwise require a long drive. Several major health systems run formal remote second-opinion services for cancer, cardiac conditions, and complex surgical decisions, reviewing imaging, pathology, and records without an in-person visit.
Some of these programs are free to the patient, funded by the institution or a research grant. Others charge a flat consultation fee that may or may not be reimbursed by insurance.
Questions to Ask Before Choosing a Remote Specialist
A short round of questions before booking a remote consult prevents wasted time and money.
- Does the specialist have direct experience with this specific diagnosis or procedure, not just the general field?
- Will the review include the actual imaging and pathology, or only written reports?
- Is the service billed to insurance, charged as a flat fee, or free through a research or nonprofit program?
- Will the specialist coordinate directly with the local treating physician afterward?
- How long does a typical review take from submission of records to a written opinion?
When to Seek Immediate Care Instead of Waiting for Another Opinion
Sudden, severe, or rapidly worsening symptoms call for immediate care rather than a delayed second opinion. Chest pain, stroke symptoms, uncontrolled bleeding, or a sudden change in a known condition need emergency evaluation first; a second opinion on the underlying diagnosis can follow once the patient is stable.
Second opinions serve non-emergency decisions best, such as confirming a cancer diagnosis, weighing surgical options, or reviewing a treatment plan for a chronic condition. Waiting on a second opinion when a condition is actively deteriorating carries real risk that outweighs the value of an additional viewpoint.
Expanding Access Makes Safer Decisions Possible
Fewer specialists in a region does not have to mean fewer independent opinions. Academic medical centers, virtual second-opinion programs, and clearer insurance pathways are closing part of the gap that geography once made absolute.
Patients in low-density specialist markets who ask directly for an out-of-network referral, gather their full records early, and consider a remote review stand a real chance of getting the outside look that changes a diagnosis or treatment plan in a meaningful share of cases. The tools for reaching an independent specialist now extend well past the local hospital system, and using them starts with a direct request rather than a wait-and-see approach.